The UK records a further 649 deaths, taking the total number of coronavirus deaths to 30,076.


The UK records a further 649 deaths, taking the total number of coronavirus deaths to 30,076.
University of Virginia researchers are pioneering the use of focused ultrasound to defy the brain’s protective barrier so that doctors could, at last, deliver many treatments directly into the brain to battle neurological diseases. The approach, the researchers hope, could revolutionize treatment for conditions from Alzheimer’s to epilepsy to brain tumors — and even help repair the devastating damage caused by stroke.
Richard J. Price, PhD, of UVA’s School of Medicine and School of Engineering, is using focused soundwaves to overcome the natural “blood-brain barrier,” which protects the brain from harmful pathogens. His approach aims to breach the barrier only where needed, and only when needed, and then deliver treatments in exquisitely precise fashion.
“The blood-brain barrier is one of the greatest, if not the greatest, challenge to drug delivery for the central nervous system,” Price explained. “Evolution gave us this barrier because the central nervous system needs to be protected. The problem is now we want to deliver something to those cells and evolution has had millions and millions of years to optimize a solution to stop it. … So I’m attempting to circumvent biology with physics.”
Focused Ultrasound’s Great Potential
Focused ultrasound focuses sound waves inside the brain much like a magnifying glass can focus light, letting doctors manipulate tissue without cutting into the skull. Magnetic resonance imaging (MRI), meanwhile, lets them watch what’s happening inside the brain in real time. While Price, a biomedical engineer, is developing his techniques in the lab, doctors are already using the technology to treat conditions such as Parkinson’s tremor.
Price marvels at the approach’s specificity. “With MRI, we can look at the target, whether it’s a brain tumor or maybe it’s a part of the brain we want to do gene therapy on, and we can select it — we can actually make a treatment plan and say, We only want to open the [blood-brain] barrier there. The other 95% of the brain, we don’t even touch,” said Price, the research director at UVA’s Focused Ultrasound Center. “Then, when we apply the focused ultrasound, it opens the barrier there for a few hours. It lets us get the gene therapy across, and then it closes naturally.”
Delivering Gene Therapy
Gene therapy introduced via focused ultrasound would essentially reprogram faulty cells.
For brain tumors, Price is exploring the potential of using focused ultrasound to deliver gene therapy via “deep-penetrating nanoparticles.” The nanoparticles, designed by Price’s collaborators at Johns Hopkins University, “are specifically engineered to penetrate the tissue extremely well,” he said. The problem has been transporting them where they’re needed, often deep inside the brain, and Price says focused ultrasound holds the answer.
His solution is to use the focused soundwaves to open spaces between cells in the tissue. “It doesn’t help us if you can’t get to the neuron that’s 50 microns away,” he said. “So that becomes an engineering transport problem.”
In addition to delivering the therapy, focused ultrasound can “precondition” targeted tissue to enhance the effectiveness of the gene delivery up to five-fold, Price has found. The preconditioning represents a “simple and effective strategy” to boost the benefits of the nanoparticles, he and his colleagues report in a scientific paper.
Improving Stroke Outcomes
For stroke, a condition that is often debilitating when it’s not deadly, Price aims to help the brain heal itself. He would do this by using focused ultrasound to put “homing molecules” inside damaged areas to recruit neural stem cells to do repairs. For this, his team has developed an innovative technique called “sonoselective transfection” that avoids opening the blood-brain barriers in brains that are already compromised.
“With stroke, there’s a lot of effort to try to salvage as much neural tissue as possible by doing things like gene therapy,” he said. “In our lab, we thought, well, maybe we can deliver treatment right to the cells that need it, without breaching the blood-brain barrier. And my students basically figured out how to do that.”
That notion of helping the body heal itself, of using focused ultrasound to activate an immune response, could be useful in cancer treatments as well. “We would love to be able to put something into those [tumor] cells that will then allow them to start recruiting immune cells into the tumor,” he said. “We have a lot of evidence that we can we can do some interesting things with focused ultrasound with respect to the internal landscape of those tumors.”
Price, of UVA’s Department of Biomedical Engineering, emphasizes that his work is still early, but he is excited to be creating new techniques that could change how many major diseases are treated in the not-too-distant future.
“We’ve had good results [with the research] so far. But what I, as an engineer, get excited about are all these tools we have made,” he said. “You can use these tools for all these different applications. We think there are a lot of really exciting possibilities.”
The human gut microbiota consists of trillions of bacteria, fungi and virus constituting an inner chemical factory producing a multitude of microbial compounds affecting immunity, neurobiology and metabolism of the human host.
It has for long been known that imbalances in the composition of gut microbes link with a variety of chronic human disorders spanning from obesity, diabetes inflammatory bowel diseases to depression, schizophrenia, autism and Parkinson. In addition, it is known that unhealthy dieting and use of some medications, for instance stomach acid neutralizers, the so-called proton pump inhibitors, are associated with a further disruption of the microbial communities of the gut.
Now, in a new paper in the scientific journal Nature, The MetaCardis investigators explore gut bacteria in almost 900 individuals from Denmark, France and Germany.
The intestinal microbiota in obese individuals had previously been shown to differ from those in lean subjects with a poor bacterial diversity, a relative depletion of health promoting bacteria and the remaining bacteria dominated by an inflammatory tone.
In their Nature article, the researches now define a cluster of bacteria called Bact2 enterotype, which is found in 4% of lean and overweight people but in 18% of obese individuals who did not use statin drugs, a group of cholesterol lowering medications.
However, in other obese study participants who were treated with statins, the prevalence of the unhealthy Bact2 enterotype was significantly lower (6%) than in their non-treated counterparts (18%) — comparable to levels observed in non-obese participants (4%). The same trend was validated in a Flemish study sample of about 2000 participants.
Statins are commonly prescribed to reduce risk of developing cardiovascular diseases like myocardial infarction and stroke. It is estimated that more than 200 million people worldwide are prescribed statins. Besides their cholesterol-lowering effects, statins also tend to appease patients’ systemic inflammation levels which in part may be related to a disrupted gut microbiota.
The results suggest that statins could potentially modulate the disrupted gut microbiota and linked inflammation in obesity. Previous experiments in rodents have shown an impact of statins on bacterial growth, which might benefit non-inflammatory bacteria and underlie the anti-inflammatory effects of statin therapy. Obviously, clinically controlled human trials are needed to address whether statins mediate some of their anti-inflammatory effect via an improvement of the Bact2 enterotype of an aberrant gut microbiota.
Story Source:
Materials provided by University of Copenhagen The Faculty of Health and Medical Sciences. Note: Content may be edited for style and length.
Hexavalent chromium continues to contaminate water sources around the world, with one US company fined just this February for having put employees at risk. Hexavalent chromium is considered to be extremely toxic, especially when inhaled or ingested, and its use is regulated in Europe and in many countries around the world. It is thought to be genotoxic, leading to DNA damage and the formation of cancerous tumors.
Now, chemists at EPFL are developing energy efficient processes for removing contaminants, this time hexavalent chromium, from water. The results are published today in the Journal of Materials Chemistry A.
“Providing access to clean water is one of the most important challenges of our time,” says lead author Wendy Queen of EPFL’s Laboratory of Functional Materials. “The development of energy efficient processes able to rapidly remove water contaminants play an important role in our effort to globally improve human health and environmental well-being.”
Queen and colleagues are developing sponge-like materials that can collect specific substances from solution. Their materials are actually crystals, called metal-organic frameworks (MOF), and the scientists are tailoring these crystalline structures to capture a particular substance.
The materials are extremely porous and the contact surface area contained in one gram of these MOFs can be as large as that of a football field. The target substance then enters these pores and sticks to the internal surface area in a process called adsorption.
The scientists have previously shown that their materials can efficiently adsorb other substances dissolved in solution, like gold, mercury and lead. For instance, 1 gram of MOF yields almost 1 gram of gold. Queen, in collaboration with EPFL scientist Berend Smit and EPFL PhD student Bardiya Valizadeh, has demonstrated the extraction of hexavalent chromium from water. With hexavalent chromium, a relatively light substance, the MOFs can extract approximately 208 milligrams per gram of MOF. Also, if you shine light on the MOF, it then transforms the highly toxic hexavalent chromium into a relatively nontoxic trivalent chromium.
Further developments are required in order to implement the technology for decontaminating water outside of the laboratory.
“The great thing about our sponges is they are relatively easy and cheap to make,” explains Queen. “The next step is to test our sponges at larger scales.”
For example, the scientists expect 1 kg of MOFs to cost roughly 15 CHF to make, whereas 1kg of gold is worth roughly 55,000 CHF.
Story Source:
Materials provided by Ecole Polytechnique Fédérale de Lausanne. Note: Content may be edited for style and length.

When she gets home in the afternoon, physician Dr Arifa Parker disposes of her work clothes in the washing machine. She then has a thorough shower before greeting her three-year-old twin toddlers, Yusra and Haniya, with a hug.
Since January, Parker has served at the coalface of South Africa’s fight against Covid-19. One of three infectious diseases specialists at Cape Town’s Tygerberg Hospital, she treats patients positive for the coronavirus in specially set-up wards; supporting Intensive Care Unit staff, and screenings in a tent set-up on the premises. Meanwhile, she is also gathering information and formulating protocols for how to best tackle this pandemic.
This week, 39-year-old Parker opened up to Spotlight about being a doctor and a mother in the eye of the Covid-19 storm. Speaking via a Zoom interview, her sentences are laced with laughter, despite the gravity of the task ahead of her.
“I’m very careful,” she says. “I know what the risks are and when I see my patients, I make sure that I wear adequate PPE – personal protective equipment. And that is what I tell the junior staff as well. No one should be seeing patients without adequate protection. We do have enough stock for now, if we use it wisely; and more has been ordered,” Parker says.
“So that makes me feel better going home to my kids. The hospital is frantically working on shower facilities for staff, so we could take a shower and change into normal clothes before going home. For now, I jump into the shower and wash my clothes before giving my little ones a hug. So that is a bit odd, because they usually would jump into my arms immediately when I get home.”
Fortunately, Parker’s husband Ghaliel, who works in IT, is taking care of their young children during lockdown. “He’s been amazingly, amazingly supportive,” she says. “He’s been working from home via Zoom, with the kids in the background.”
Parker’s early training is in HIV and tuberculosis (TB). After completing a medicine degree at Stellenbosch University, she did her internship at GF Jooste Hospital in Manenberg on the Cape Flats, under renowned mentor Professor Graeme Meintjes. This was in 2005, a year after antiretroviral (ARV) drugs were first starting to be rolled out by the state in South Africa, after a lengthy struggle by civil society for access to treatment.
“At the time it was quite overwhelming because ARVs were not freely available and a lot of young people were dying,” recalls Parker. “Manenberg was my first choice, because it was a hospital in an impoverished community. I wanted to help people. So I ended up doing my community service the following year in Khayelitsha as well,” Parker tells Spotlight.
“You know, as interns, we used to have to fill in the death certificates. So you would have the deceased patient in front of you, and you’d look at the ID photo and it would show someone so different to the completely ravaged patient. And that’s why I ended up doing internal medicine and infectious diseases, because I wanted to understand a bit more about how the body works and how one would be able to treat these patients better. And fortunately, with the ARV rollout, HIV patients are now doing so much better. And you know, it’s actually quite rewarding to work in the field of HIV medicine. But we still have a lot of work to do; we still have to roll out more ARVs and prevent lots of infections. We still have lots of challenges. TB and everything else.”
Parker pauses, as her phone rings. She excuses herself to answer it. Then, turning back to the interview, she adds: “And now there’s Covid-19 thrown into the mix, too.”
On 11 January, Chinese state media reported the first known Covid-19 related death. Since then Parker has “lived and breathed” coronavirus.
“So Covid didn’t exist to us before January,” she says. “We heard about it mid-January; and then we started having to prepare for cases, having to put procedures and systems in place. So as infectious diseases specialists, we’ve had to educate ourselves, rapidly. We’ve had a steep learning curve and part of that has been adapting to create standard operating procedures for our hospital.
“Also we don’t know – internationally – what the effect of Covid will be on our HIV-positive patients. There were very few patients in China who had HIV. You know, there are lots of questions.”
At night, Parker sits in bed next to her husband working and reading; sometimes she works in their kitchen over a cup of tea. They take turns to cook: butter chicken, lamb curry, pasta and salads. The kids go to bed at 7pm, and at 9pm she goes back to the drawing board.
“Since January, my days have all blurred into one,” she says. “Most days I can’t remember what day it is. I start quite early. I haven’t been sleeping much since the start of Covid, I mean this morning I woke up at 4:30 am. As you know, Covid is a new infection, with new data coming out all the time. So the first thing I do is look at my phone. I get lots and lots of messages, so I read the new things and send them on. My workday at the hospital starts at 8 am. At 9 am we have what we call a Covid ops meeting, where all our hospital’s heads meet – you know, radiology, surgery, anaesthetics, ICU, and so on.”
She gets home at around 5 pm – well, it depends. “For example,” she says, “last Friday at 4 pm, 200 people suddenly rocked up at the hospital’s testing centre at one time. I mean, you can’t just leave junior staff alone. So, a few of us senior staff, the paediatric infectious diseases specialist, our head of clinical medicine, and another internal medicine consultant, stayed behind and helped out and assisted in doing the tests.”
While Parker cannot comment on patient figures, she says at present Tygerberg has two general wards full, and is ready to activate more. She is quick to deflect praise, crediting her team and colleagues.
“It’s not just an infectious diseases response,” she says. “We are only three, too few people. It’s been a hospital response from all departments. I feel so privileged to be working with such amazing people at my hospital. If work needs to be done, everybody pitches in. All sorts of hierarchy have flown out the window. For example, we had the head of nephrology (renal medicine) come down and doing swabs on patients. The plastic surgery registrar does shifts; we’ve had radiology specialists coming down to assist with screenings. The anaesthetic department has been very helpful. Intubation of the ill patients is obviously a very high-risk procedure, because you would be in direct contact with the patients’ airways. And they happily put together a call roster of who will assist us should we need to do such procedures, because they are the best trained to do the intubations.”
Parker points out that the demographics of the Covid outbreak are changing. Initially, transmission was travel-related. Now healthcare specialists are seeing the early stages of community transmission. Of great concern is increasing transmission to essential workers.
She notes a spike in infections in Khayelitsha. According to provincial statistics released by Western Cape premier Alan Winde on April 28, there were 205 confirmed Covid-19 positive people in Khayelitsha.
“Last week, my direct boss, Neshaad Schrueder, and I went to Khayelitsha Hospital,” she says. “We were very concerned about the spike in Covid numbers and wanted to see how Tygerberg could support the hospital. Yes, and I think they have an excellent team of staff. They’ve put amazing systems in place; they’ve also started a tent for testing outside the hospital, and within the hospital they’ve identified separate spaces where they can keep persons isolated from each other. So we were able to help with that,” she says.
“We’re also advising hospitals that we need to work together. So, if they are seeing that they are overrun with patients, they shouldn’t hesitate to call us. Because it’s pointless having open beds in one hospital while another is full. Because we know Covid sort-of attacks areas. You’ll have fires of outbreaks; so one area might have more cases, especially at this point in the outbreak.”
On 29 April, Cape Town community newspaper TableTalk reported that two employees at Checkers Bayside – Sindoswa Msiwa of Khayelitsha and Sylvia Gaxela from Delft – succumbed to Covid-19. The newspaper quoted Msiwa’s brother, Luthando, as saying: “My sister worked on Sunday, 12 April even though she wasn’t feeling well. She called me that evening saying she wasn’t well, and I took her to Khayelitsha Hospital where she tested positive. She was later transferred to Tygerberg Hospital, where she stayed in intensive care. She died on April 12.”
Asked about Msiwa’s death at Tygerberg, Parker notes that she is not allowed to comment on individual patients due to patient confidentiality. “This is so sad,” she says. “My thoughts are with the family. It’s very sad, but it is inevitable that people will die. I see some of my colleagues are struggling with this, but there is nothing more they can do. As healthcare workers, we shouldn’t be too hard on ourselves.”
Can the pandemic still be contained in South Africa? “Um, obviously we’re worried,” says Parker. “I don’t think we can entirely eradicate Covid. I think it will still be a problem, but I think it’s imperative that we try to prevent cases. If we don’t, more people will die and our hospitals will be overrun with cases. So, it’s still very important that we test, test, test, and when we find cases, that we try to isolate. We are obviously very concerned about overcrowded areas, and that is why the country has rolled out community testing.”
While government is under fire from some quarters for its lockdown regulations, Parker insists these measures are crucial. “My personal opinion is that the lockdown was an excellent decision, because it gave our hospital and other hospitals time to prepare, time to make sure that staff are educated on how to use PPE; time to create ward and intensive care space; and to create the documents that we are working on at the moment,” Parker says.
“I am so fortunate that we have had a chance to work on those. I just think of the poor healthcare workers in China and Italy who didn’t have a chance to prepare; they didn’t know what hit them. Fortunately, we have systems that are in place now that can hopefully help to relieve the burden on our healthcare force.”
She says healthcare workers are rethinking the way they practice medicine in the time of Covid-19. This includes less touch.
“We have to minimise risk while assessing and managing patients,” she says. “For example, something that would normally take five minutes now takes ten minutes. You need to know exactly what you are going to do for the patient when you go into his or her ward. As physicians, we love to spend time with patients. We love to feel, touch, and to thoroughly examine everything. But I think we need to sort of rethink the way we practise medicine in the time of Covid. Having an additional layer of awareness. We have to touch less and think: ‘If I touch this, is it going to contribute to my management of a patient. If I spend hours listening to every part of the lung, would it give me more information than the chest X-Ray that we already did?’ I would not have said this in December, but now with Covid, obviously we have to change the way we practise medicine, which may be a bit controversial.”
“Our patients have been amazing,” says Parker. “I’ve also learned new things about technology, communicating via cellphone, you know, phoning the patients and taking their history like that, asking them if they are okay. I have renewed respect for social media; this is really helping to keep patients in touch with their families. So, you know, somebody mentioned that maybe we should have patients not have their phones with them because they can get contaminated. That’s the worst idea. This is the way they keep in touch with family and friends, despite the lack of interaction.”
Parker adds that the public and private health sectors are collaborating in the fight. “This has been another amazing thing. We call each other for advice, it’s just been such a different experience as to how medicine normally works. And I really hope that if there is an after-Covid, that we continue this sort of enthusiasm.”
Parker grew up in Cape Town’s northern suburbs in Cravenby – which happens to be near Tygerberg Hospital – where she matriculated at Cravenby Secondary School. “We had amazing teachers, who shaped and opened our minds,” she says. “The motto of the school was ‘aim high’, so, well, we aimed high.”
One of five children, Parker’s youngest brother studied medicine too, and is presently completing an internship at Kimberley Hospital. “Oh, my parents never forced us to do anything,” she says. “My mom’s brother is a doctor, but there’s no real family history of healthcare. My parents did encourage hard work.”
On her sunny disposition, she says: “I think negativity is a wasted emotion. I think if you find that there are issues or that you find something negative or you’re not happy about something, it may be more constructive to come up with a solution to that problem. That’s just my approach. If something is broken or seems to be broken, try to fix it instead of complaining about it.”

The PM says government is “working hard” to tackle it – and sets 200,000 test aim by end of month.
A study has identified a mutation that its authors say could make the coronavirus more infectious.
I love the morning magical time. It’s my favorite time of day – before dawn when most of the city is still snug in bed.
This morning I hopped out of bed at 4:45am, feeling happy to start another adventurous day. By 7am this morning, I had done the following:
Afterwards I reviewed my goals, and now I’m sipping the smoothie and writing this blog post while the oatmeal is cooking and the robot is diligently cleaning the kitchen floor.
Caffeine isn’t part of my day by the way, nor is chocolate, caffeinated teas, or other stimulants. That would just slow me down.
When I was 20 years old, this is what my morning would have looked like this (sometimes all the way to noon and beyond):
Then I’d drag myself out of bed and start my day very sluggishly. It would take me at least an hour or two just to feel awake enough to function much at all. Then the rest of the day would be a blur, with the main decisions being figuring out what to eat. My biggest accomplishment of the day would be going for a long walk. At least I liked to walk.
What made the difference? Really it came down to a decision. I decided I didn’t want to live like that first person anymore. I didn’t want his life or his results – because they sucked! It was a boring, low energy, depressing way to live. And I decided that I could change that.
When I would read about highly productive people and their morning routines, I was envious at first, but their routines also seemed unreachable for me. Still, I felt attracted to having an empowering morning routine and starting my day with high energy. It took a long time to figure out what works best for me. I experimented a lot.
A solid cardio workout is such an essential part of my routine because of the benefits it produces. What many people don’t realize is that cardio exercises the brain, not just the body. It makes your brain and your mind stronger. See the Mental Benefits of Cardio video for more details on that. A good minimum is 45 minutes per day.
Running 5 miles (8K) to start my day is a stretch for me. I’m used to running closer to 3 miles (5K) on a normal basis. But it feels so much better to stretch myself. The feeling isn’t 60-70% better, relative to the mileage increase. It’s more like 3x better. Running farther than usual creates a disproportionate boost in mood and energy above the baseline.
Nailing an empowering morning routine sets you up for a strong day. It’s wonderful to know that you’ve accomplished something meaningful during those first couple of hours.
I’m not in competition with anyone here. I compare my results to where I’ve been. My past self is the baseline, and as I generate new past selves, I develop new baselines. Presently I’m pushing myself to surpass my old baseline from earlier this year.
I especially like the combo of audiobooks and running. It’s nice to go through an audiobook every few days without having to take any extra time. Maybe you won’t retain every idea as well this way, but it still helps.
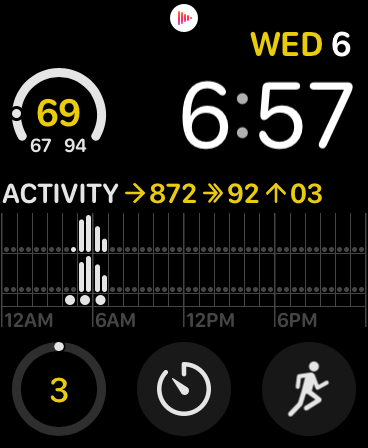
That app in the lower left of my Apple Watch screen (with the number 3 in the middle of a circle) is Nozbe. If I get a cool idea while running, I can tap that app and record a quick voice message that will go into my capture system as text. So if I do catch a cool idea from an audiobook while running, I send it into my system while on the road, and then I can decide if I want to turn it into something actionable later that day.
What’s the best morning routine you’ve ever had in your life? Are you at least using that as your baseline today? Now what are you doing to surpass it? Just because it’s good doesn’t mean you should settle. How could you make it even more kickass?
My morning routine works well for me. It’s energizing and mood-boosting. But it could be better, so I’ll keep tinkering with it and improving it over time. There is no reason to settle for good enough.

The virus that causes Covid-19 typically strikes the lungs with full force, but new research shows it can also cause frostbite-like patches on the hands and toes, and rashes on the body.
The condition has recently been dubbed “Covid toes”. Fortunately, it isn’t serious and the lesions usually disappear on their own, said Dr Esther Freeman, director of Global Health Dermatology at Massachusetts General Hospital in Boston.
“One of the more surprising findings in this epidemic has been the lesions that we’re seeing on people’s toes and hands,” she said.
Freeman noted that Covid toes aren’t caused by exposure to cold, as is frostbite or chilblains. Rather it seems to be an inflammation of the circulatory system that shows up as a skin rash.
“It’s really important to reassure the public that most of our patients who are developing Covid toes are doing very well, so they’re often patients who have a benign clinical course. They either are having mild disease or often their only symptom might be their toes,” she said.
Freeman said that Covid toes don’t just happen to children, as some have believed – adults also get them.
Should you develop Covid toes, you’re not likely to end up in an intensive care unit. “That’s not what we’re seeing in the data,” said Freeman.
Skin rashes aren’t always associated with viruses, but measles, herpes and chickenpox are conditions where skin eruptions are the main symptoms, so it’s not unheard of, Freeman noted.
She can’t say how common Covid toes are because the data that would include the number of cases of Covid-19 and Covid toes doesn’t exist. Freeman is compiling a registry of known Covid toe cases.
Anecdotally, she’s seeing a lot more cases than usual. “In addition to running the registry, I see patients myself through tele-dermatology at Massachusetts General Hospital, and I have seen more toes in the past two weeks than I have in the rest of my career,” Freeman said.
If you have what you think might be Covid toes, don’t panic, Freeman said. Don’t rush off to the emergency room, but don’t ignore it either. The best thing to do is contact your doctor or dermatologist, she added.
Also, don’t try to get a Covid-19 test. “You should talk to your healthcare provider and decide the risks and benefits for your particular case. It’s important to go by local testing guidelines. It’s not as simple as a yes-no, but I think that it should be considered a Covid-19 infection,” Freeman said.
Dr Raman Madan is a dermatologist at Northwell Health Huntington Hospital in Huntington, New York. He said, “Covid toes is the most common finding I have seen in patients via tele-dermatology. It is a fairly new symptom that we usually do not see with a lot of viruses.”
Traditionally, the condition would result from being out in the cold for a long time or having a rheumatologic problem, he said.
“With Covid-19, I have been seeing it in a lot of young, healthy people. There is still a lot to be learned,” Madan said.
A lot of patients have been asymptomatic aside from the toes and have been testing negative on their viral culture, but positive on their antibody test, Madan said.
“This has led me to believe that this may occur at the convalescent stage of illness, meaning after the body has cleared the virus. We are still working on the best guidance to give patients,” he said.
Two recent reports detail cases of Covid-19 and show that hands and toes aren’t the only places rashes appear.
In one, researchers described a patient in Wuhan, China, with Covid-19 who developed a rash on the torso. The researchers believe the rash was caused by an immune response to the virus and the patient tested positive for the Epstein-Barr virus, which has been tied to Covid-19. The rash disappeared within a week, but the patient died from Covid-19.
In the second case, a Spanish man suffering from Covid-19 developed a rash on his thighs and buttocks. The rash went away after five days and the patient left the hospital after 12 days. The researchers assume that the rash was a reaction to the virus.
“Dermatologists should be aware that patients presenting with this kind of rash, in addition to coughing and fever, could benefit from [Covid-19] testing,” said lead researcher Dr Borja Diaz-Guimaraens, from the dermatology department, Ramon y Cajal University Hospital in Madrid, Spain.
“We are starting to notice more extra-respiratory manifestations in patients with confirmed Covid-19, and increased awareness for those signs can help diagnosis,” he said.
The two case reports were published online in JAMA Dermatology.
READ | Coronavirus 101 – here’s what you need to know
READ | Is Covid-19 now linked with strokes in young patients?
READ | Coronavirus hangs around even after symptoms subside

Most patients recover from Covid-19 quickly – but for some, symptoms linger for weeks.
